
Key Takeaways
- Xanax to Valium conversion replaces alprazolam with diazepam in stages at the start of a benzodiazepine taper, usually beginning with the evening dose.
- Diazepam is long-acting, so its blood level stays steadier between doses than alprazolam’s, and a taper is easier to control from that steady baseline.
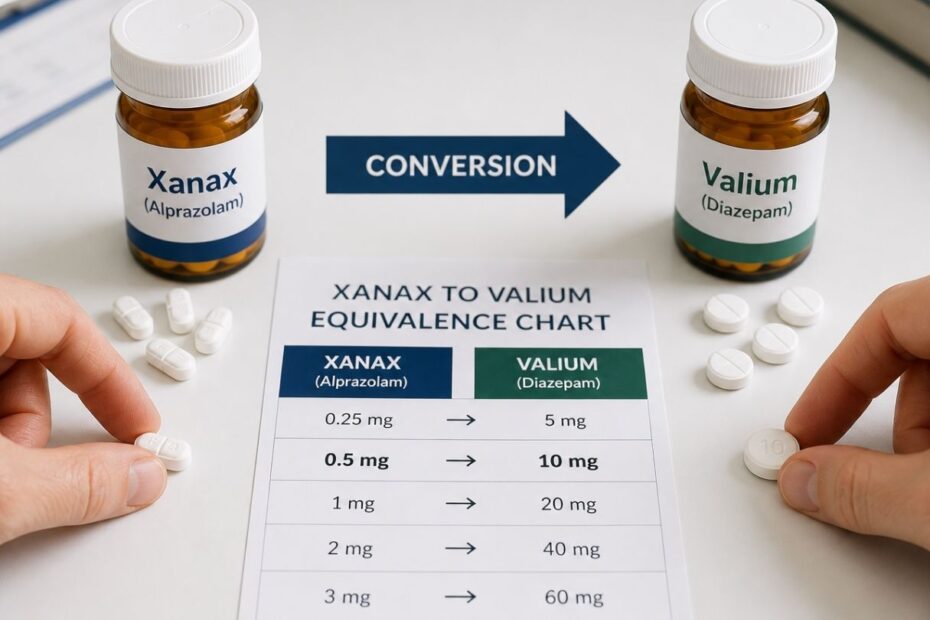
- The Ashton Manual treats alprazolam 0.5 mg as approximately equivalent to diazepam 10 mg, and the physician adjusts that figure to the person.
- In the Manual’s alprazolam schedules the earliest stages involve substitution only, reductions during the later stages of the switch are a feature of high starting doses, and the main reduction phase follows once diazepam has replaced Xanax.
- Each stage is held until it has settled, so the pace follows the person’s response rather than the calendar.
- A crossover changes two prescriptions at every stage, which is why it belongs entirely under a prescribing physician’s supervision.
- Dependence on Xanax taken as prescribed is physical dependence, not addiction, and the crossover is a medical technique within a gradual taper.
- Brief daily notes on sleep and symptoms tell the physician whether a stage has settled or needs more time.
Xanax to Valium conversion is the stepwise replacement of alprazolam (Xanax) with diazepam (Valium) at the start of a benzodiazepine taper. The Ashton Manual describes this crossover for people coming off short-acting benzodiazepines: diazepam is substituted in stages, the earliest stages involve substitution only, and modest reductions of the total dose begin during the later stages of the switch, with the main reduction phase following once diazepam has replaced alprazolam. This article explains why the conversion is used, how it proceeds in practice, and what the Ashton Manual’s equivalence between the two medications actually says. It is educational information, not medical advice: a crossover involves prescription decisions at every stage and belongs entirely under the supervision of a prescribing physician.
Why Conversion Is Used in Benzodiazepine Tapering
The case for conversion comes from the difference between the two medications. Xanax is potent and short-acting: its blood level rises and falls quickly, and between doses the level can drop far enough for withdrawal symptoms to appear. Diazepam is the opposite in the way that matters here: it is long-acting, and its slow decline keeps the blood level comparatively smooth from dose to dose. For someone preparing to taper, that smoothness is the point. A taper is a controlled descent, and it is far easier to control from a steady baseline than from a level that swings several times a day. Diazepam is also available in smaller dose strengths, which makes the small, precise reductions of a gradual taper practical. Most people weighing a conversion became dependent on Xanax by taking it exactly as prescribed. Physical dependence is a predictable medical condition, not addiction, and the crossover is a medical technique within a gradual taper, not a treatment for addiction. The pharmacology behind the switch is covered in this site’s article on Valium cross-tolerance and diazepam equivalency in medication switching.
What Is Xanax to Valium Conversion in Practice?
The Ashton Manual’s method is stepwise. A person taking Xanax several times a day does not switch everything at once. Substitution proceeds in stages, usually beginning with the evening dose, and often a portion of a dose at a time: in the Manual’s alprazolam schedule, 0.5 mg of the evening alprazolam is replaced by 10 mg of diazepam, and at the next stage another 0.5 mg is replaced, with the other doses unchanged until their turn comes. When one stage has settled, the next follows, until diazepam has replaced Xanax entirely. The equivalence the Manual gives anchors these substitutions: alprazolam 0.5 mg is approximately equivalent to diazepam 10 mg. Two things about that figure deserve emphasis. It is an approximation, and individual responses vary, so the physician watches how each substitution lands and adjusts. And it shows why the conversion must be done knowledgeably: the milligram amounts involved are very different, and treating the two medications as interchangeable milligram for milligram would be a serious error. The Manual does not keep substitution and reduction strictly separate. Its own schedule notes that the first four stages involve substitution only, with no actual withdrawal, and that some dosage reduction occurs in the later stages of the switch. The main reduction phase then follows once the person is stable on diazepam alone. The mechanics of the substitution itself are described in more detail in How Diazepam Substitution Works.
How Xanax Conversion Supports a Structured Taper
Once the crossover is complete, the taper gains structure it could not have had on Xanax alone. The baseline is steadier, so the effect of each reduction is easier to read: a symptom change after a cut is more likely to mean something about the cut, not about the hour of the day. Diazepam’s smaller dose strengths allow reductions to be modest and precise, and to become proportionally smaller as the total dose falls, the shape both the Ashton Manual and the Maudsley Deprescribing Guidelines describe. The usual rhythm of a gradual taper then applies: a small reduction, time to settle, attention to symptoms, and a hold whenever the nervous system asks for one. Improvement tends to move in windows and waves, better stretches with temporary returns of symptoms, so the trend over weeks matters more than any single day.
The Role of Professional Guidance in Conversion
A crossover is the least do-it-yourself part of benzodiazepine tapering. Each stage changes two prescriptions at once, and there are judgment calls at every point: how much to substitute at each stage, how long to stay there, and how to read the symptoms in between. Too much diazepam too quickly produces oversedation; an incomplete substitution lets withdrawal through. People also differ in how they process diazepam, and those differences are exactly what physician supervision exists to catch. The Ashton Manual, written by the late Professor C. Heather Ashton of Newcastle University, provides the framework: stepwise substitution, approximate equivalence, patience between stages. The physician’s work is fitting that framework to one person. The figures the framework rests on are explained in The Ashton Manual Benzodiazepine Equivalence Table Explained.
Building Confidence Through a Personalized Plan
A conversion plan looks intricate from the outside, and unexplained intricacy feeds fear, which amplifies withdrawal symptoms. Understanding the sequence, substitution in stages, stability at each stage, and gradual reduction that begins modestly and then becomes the main work, replaces a frightening unknown with a process that has a visible shape and known resting points. The taper calculator on this site can make conversion and tapering details easier to picture as part of a clear, physician-guided plan. Like any planning tool, it illustrates the method; the actual doses and timing are set with the prescribing physician.
The Importance of Consistency and Monitoring
Crossover stages land best on a consistent routine. Doses at the same times each day, prescriptions filled at one pharmacy, and the same manufacturer where possible all keep the variables down, and a sensitized nervous system notices variables. Monitoring during a conversion is simple and specific: brief daily notes on sleep, symptoms, and how each substitution stage felt. That record tells the physician whether the current stage has settled, whether the next one should wait, and whether the equivalence needs adjusting for this individual. Symptoms during a stage are information, not failure, and a stage that needs more time gets it.
Frequently Asked Questions
How do you convert Xanax to Valium for tapering?
In stages, under a prescribing physician’s supervision. Part of one of the day’s Xanax doses, usually the evening dose first, is replaced with an approximately equivalent amount of diazepam; when that substitution has settled, the next portion is converted, and so on until diazepam has replaced Xanax completely. In the Ashton Manual’s schedule the earliest stages are substitution only, modest reductions begin during the later stages of the switch, and the main reduction phase follows once the crossover is complete.
How much Valium equals a dose of Xanax?
The Ashton Manual’s equivalence table treats alprazolam 0.5 mg as approximately equivalent to diazepam 10 mg. The figure is an approximation rather than a rule: individual responses differ, and the supervising physician adjusts the substitution based on how each stage actually lands.
Why do doctors switch from Xanax to Valium for tapering?
Because diazepam’s long action holds the blood level steadier between doses, which removes the swings and interdose withdrawal that make Xanax difficult to taper directly. Diazepam’s smaller available dose strengths also make gradual, precise reductions practical. This is the crossover approach described in the Ashton Manual.
How long does the Xanax to Valium switch take?
There is no fixed timetable. The substitution proceeds in stages, each held until the person is stable, commonly over a period of weeks and sometimes longer. The pace follows the response rather than the calendar, and the main reduction phase begins once the final substitution stage is complete.
Are Xanax and Valium taken together during the crossover?
Yes, for a time. In the staged form the Manual describes, part of one of the day’s Xanax doses is replaced by diazepam while the other doses stay unchanged, so for a period of weeks a person takes both medications, with the Xanax share shrinking at each stage. Each stage changes two prescriptions at once, which is one reason the conversion is the least do-it-yourself part of tapering and stays under a prescribing physician’s supervision until diazepam has replaced Xanax entirely.
What if the switch leaves you too sleepy, or still in withdrawal?
Both are signs that a stage needs adjusting, not signs of failure. Too much diazepam too quickly produces oversedation, and an incomplete substitution lets withdrawal through, because the equivalence is approximate and people differ in how they process diazepam. The Ashton Manual’s aim for the switch is a dose of diazepam that largely prevents withdrawal symptoms but is not so excessive as to make you sleepy.
This is what the daily notes are for. They tell the physician whether the current stage has settled, whether the next one should wait, and whether the equivalence needs adjusting for this person, and a stage that needs more time gets it.
Substitution First, Main Reduction After
The crossover exists to make the taper that follows calmer and more controllable: replace in stages, keep the ground steady, and reduce gradually, with the small reductions of the later crossover stages giving way to the main reduction once diazepam stands alone. To see how the reduction phase is typically structured after a crossover, the Xanax taper calculator on this site lays out stepwise plans. The benzodiazepine conversion calculator shows the diazepam equivalent of any dose in the Manual’s table.
This article is educational. It is not medical advice, and reading it does not create a doctor-patient relationship. Decisions about starting, continuing, or tapering any medication should be made with your own physician.
